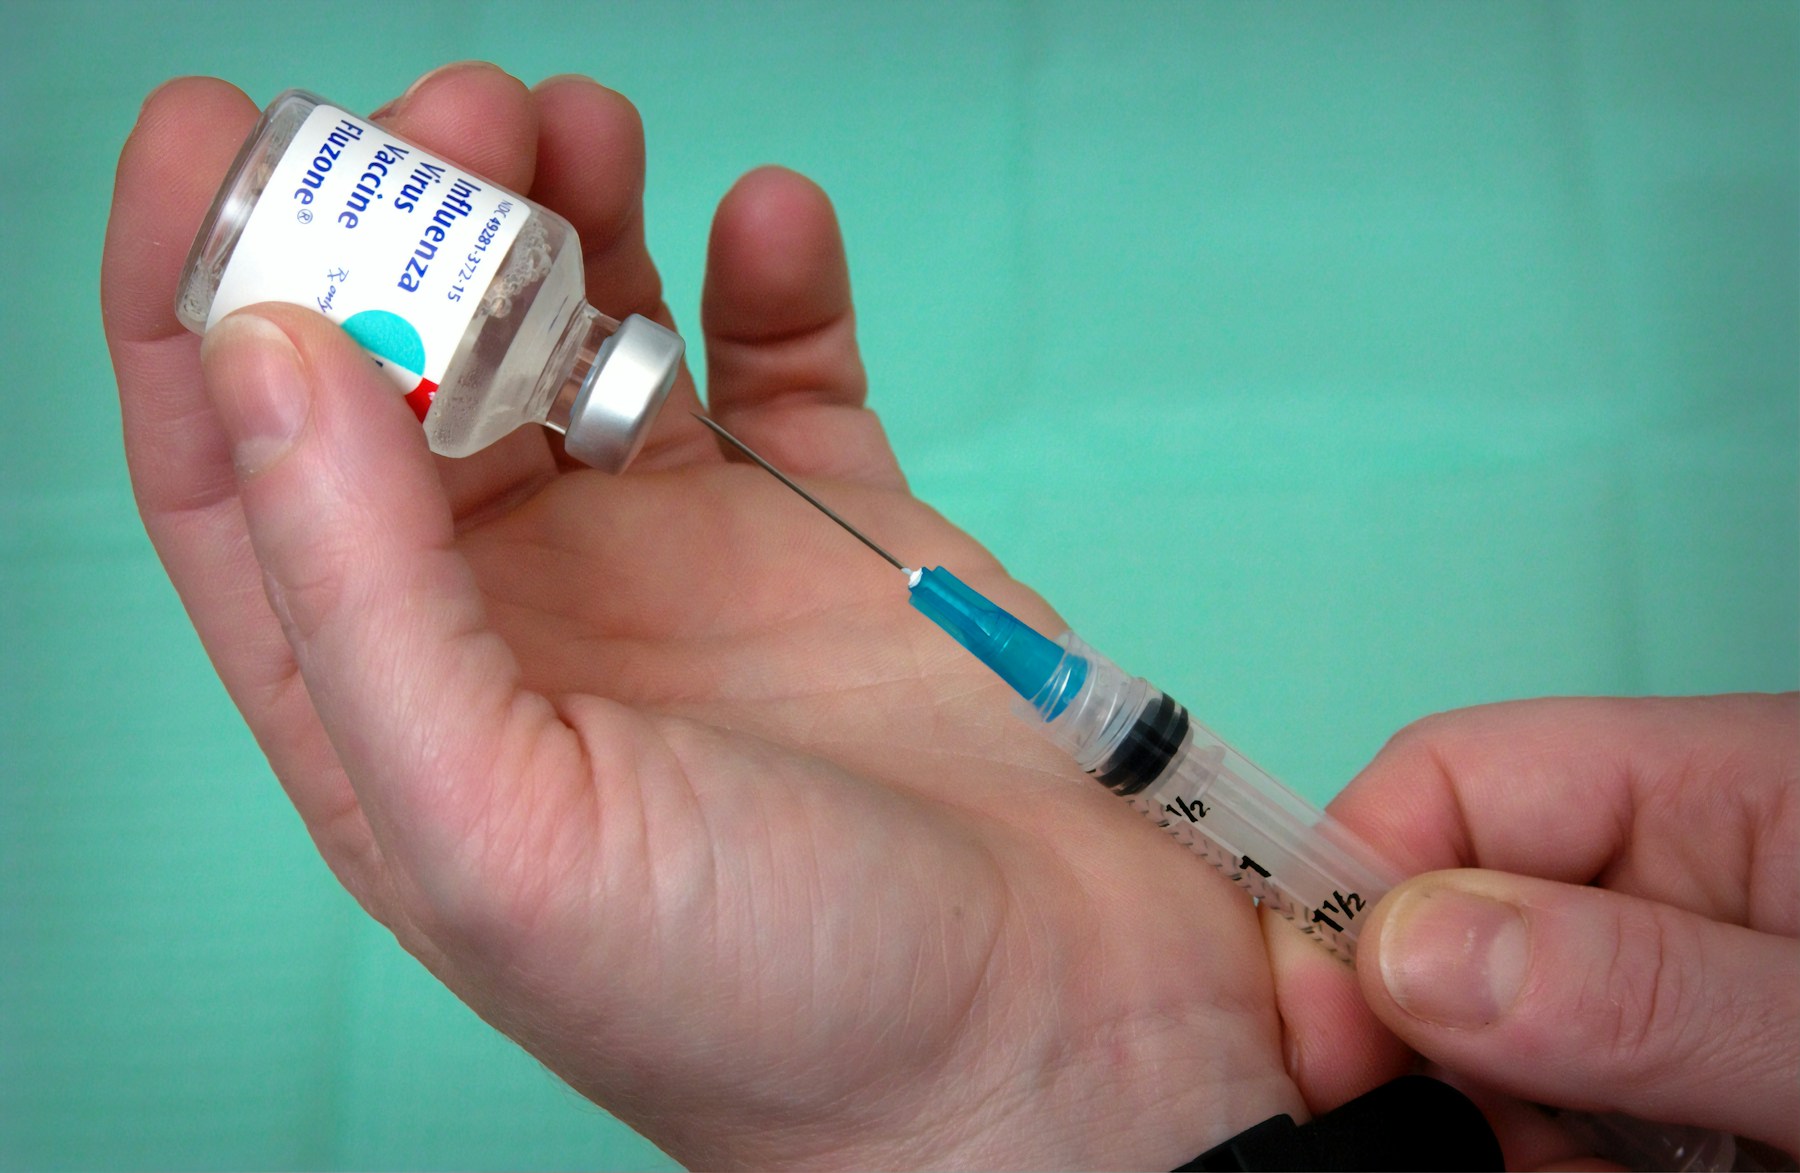
- The human evidence for the popular "healing" peptides is close to nothing. Of 36 studies of BPC-157 for muscle, tendon and bone healing, 35 were preclinical lab or animal studies. The FDA says it has found no human exposure data at all for TB-500
- "Research use only" is a label, not a safeguard. The FDA treats these vials as unapproved drugs when sellers market them for people, and no one has checked what's inside
- Lab tests of the vials are worrying. In 6,441 independent tests of 14 research peptides, 41.6% to 71.1% failed basic quality standards, depending on how strict the bar, and 15% of samples tested for endotoxin had measurable levels
- The rules are moving, but nothing is legal yet. In July 2026 an FDA advisory panel narrowly backed letting pharmacies compound six peptides, including BPC-157 and TB-500, against FDA staff advice. A formal rulemaking still has to happen first
- What to do: talk to your doctor about the actual problem — weight, an injury, low energy. Where an FDA-approved option exists, as it does for weight loss, it beats a vial from a website
A few years ago, injecting peptides was something you heard about in bodybuilding forums. Now it's a mainstream men's-health habit. BPC-157 for a sore tendon, TB-500 for "recovery", CJC-1295 with ipamorelin to nudge growth hormone, injectable GHK-Cu for skin, and — the biggest market of all — "research-grade" semaglutide, tirzepatide and retatrutide for weight loss, at a fraction of pharmacy prices. Much of it is bought online, often as a powder, from websites that print "for research use only" on the label.
This article isn't here to scold anyone. The appeal is real: injuries that won't heal, weight that won't move, and a sense that the medical system is slow. But if you're going to put something in a syringe, you should know three things: what the human evidence actually is, what's likely to be in the vial, and where the law stands after a busy 2026.
How "Research Use Only" Actually Works
A peptide is just a short chain of amino acids. Some are excellent, well-tested medicines: insulin is one, and so are the GLP-1 drugs. The gray market sells a different group — compounds that either have never been approved by the FDA, or are copies of approved drugs made outside the system.
The "research use only" or "not for human consumption" label is how sellers try to stay outside drug law: in theory they're selling a chemical to a lab, not a medicine to you. Joshua Sharfstein, a Johns Hopkins professor and former principal deputy commissioner of the FDA, put it plainly in an August 2026 interview: "Some companies try to avoid legal issues by labeling the package 'For Research Use Only,' but that really doesn't get them out of the legal requirement."
The FDA agrees. In a December 2024 warning letter to one online seller of semaglutide, tirzepatide and retatrutide, the agency wrote: "Despite statements on your product labeling marketing your products as 'RESEARCH USE ONLY' and 'INTENDED AS A RESEARCH CHEMICAL ONLY,' evidence obtained from your websites establish that your products are intended to be drugs for human use." If the product page talks about appetite, blood sugar or weight loss, the FDA treats the vial as an unapproved drug, whatever the sticker says. The agency has sent similar warnings to companies selling semaglutide, tirzepatide, retatrutide, survodutide and mazdutide labeled "for research purposes" or "not for human consumption" (FDA).
Retatrutide shows the gap best. It's a genuine, promising drug from Eli Lilly, and it is in late-stage trials — but as of Lilly's own September 2026 explainer, it "is not currently approved by the FDA and is considered an investigational medication." The company adds: "Anything sold to consumers outside of those trials is illegal, with no way to verify its safety, purity or dosing." Every vial of retatrutide you can buy online today falls into that category.
What's Known in Actual Humans
Evidence: Mostly animal studies; very little in peopleThe most important thing to understand about the popular "repair" peptides is how little of their evidence comes from people. BPC-157 is the clearest case. A 2025 systematic review in HSS Journal searched for every study of BPC-157 in musculoskeletal healing and found 36. Thirty-five were preclinical lab or animal studies. The single human study was a retrospective report: after a knee injection, 7 of 12 patients with chronic knee pain reported relief lasting more than six months (Vasireddi, HSS Journal 2025). A look-back report like that can't separate the drug from the way chronic pain naturally waxes and wanes.
When the FDA's staff reviewed BPC-157 for its July 2026 advisory meeting, they reported limited evidence of effectiveness: the only trial they found, for ulcerative colitis, was described in a meeting abstract — a 46-person study in which the drug was given by enema, not by injection (as reported by Time). The U.S. Anti-Doping Agency notes that BPC-157 "is not approved for human clinical use by the U.S. Food and Drug Administration (FDA) or any other global health authority," and it is on the World Anti-Doping list, so tested athletes can be banned for using it.
The animal work is genuinely interesting. But a tendon that heals faster in a rat is a hypothesis about people, not a result.
Popular gray-market peptides: what's been shown in people
| Peptide | Sold for | Human evidence | FDA approved? |
|---|---|---|---|
| BPC-157 | Tendon, joint and gut healing | 35 of 36 healing studies were preclinical (lab or animal); one small retrospective knee-pain report. FDA staff found one 46-person ulcerative colitis trial, reported only as a meeting abstract, given by enema | No |
| TB-500 | Injury "recovery" | FDA "has not identified any human exposure data" | No |
| GHK-Cu (injected) | Skin, "anti-aging" | FDA: "limited data in humans" on injectable use; topical cosmetic use is a different question | No |
| CJC-1295 | Raising growth hormone | 2006 placebo-controlled trials in healthy adults measured hormone levels: GH and IGF-1 rose. Muscle, fat and recovery weren't tested | No |
| Ipamorelin | Raising growth hormone | FDA cites a study with serious adverse events, including death, when given intravenously for gut motility | No |
| Retatrutide | Weight loss | Large company trials ongoing; investigational | Not yet |
| "Research" semaglutide | Weight loss | The approved drug is well tested; gray-market copies are not tested at all | Approved brand only |
Sources: Vasireddi et al., HSS Journal 2025; FDA's list of bulk drug substances that may present significant safety risks (updated April 22, 2026); Teichman et al., JCEM 2006; Time, July 23, 2026; Eli Lilly, September 2026.
The growth-hormone peptides have a little more human data, though not the kind that matters. In two randomised, placebo-controlled trials in healthy adults aged 21 to 61, a single injection of CJC-1295 raised growth hormone levels 2- to 10-fold for six days or more, and IGF-1 1.5- to 3-fold for 9 to 11 days (Teichman, Journal of Clinical Endocrinology & Metabolism 2006). That shows it moves hormone levels — not that men gain muscle, lose fat or sleep better. The FDA's safety listing for CJC-1295 notes serious adverse events including an increased heart rate and a systemic vasodilatory reaction, and for ipamorelin it cites a published study in which intravenous use for gut motility was followed by serious adverse events, including death.
The weight-loss drugs are a different story. Semaglutide and tirzepatide work, and the evidence is enormous — for the branded, FDA-approved products. A vial labelled "semaglutide" from a research website has none of that evidence behind it: the trials tested a specific product, not a word on a label.
What Lab Tests Found Inside
Evidence: Large dataset, not peer-reviewed, not a random sampleA large new dataset on what's in gray-market vials comes from an April 2026 preprint by Christopher Mendias and Tariq Awan of the Performance Medicine Institute in Phoenix. They analysed publicly posted results from Finnrick Analytics, a Texas lab where consumers and sellers send peptide samples for independent testing: 6,441 samples of 14 compounds, from BPC-157 and TB-500 to semaglutide, tirzepatide and retatrutide, made by 203 different synthesis companies (Mendias & Awan, Preprints 2026).
They judged the samples two ways. Against a standard modelled on pharmacy compounding — the dose within 90–110% of what the label says, and at least 98% pure — 58.4% passed and 41.6% failed on purity, dose or identity. Against the stricter standard often applied to manufactured peptide drugs — 95–105% of label, at least 99.5% pure — 71.1% failed.
How gray-market peptides measured up
Mendias & Awan, April 2026 preprint (not yet peer-reviewed). Samples were submitted voluntarily by buyers and sellers, so they are not a random sample of the market — sellers in particular may submit their best batches. Bars run from 0 to 100%.
Endotoxin deserves a word. It's a fragment of bacterial cell walls, and injecting it can cause fever and, at higher doses, much worse — sterile-looking powder can still carry it. Only 243 samples were tested for it, under 4% of the dataset; 30% had none detected, 55% had traces below the lab's limit of measurement, and 15% had low but measurable levels. Purity didn't predict endotoxin: a vial can test 99% pure and still be contaminated.
The authors are candid that purity, dose and endotoxin are only three of the many checks a real drug must pass. Things these tests don't look for — sterility, the specific impurities that can form when peptides are made, what happens to a vial during shipping and storage — matter just as much when the product goes into your body.
One of those is your immune system. The FDA's safety listings for BPC-157, TB-500, injectable GHK-Cu and ipamorelin all flag a risk of immunogenicity — the body reacting to the peptide, or to impurities and clumped molecules in it. ProPublica, reporting on the FDA's original 2023 decision, noted that injected peptides carry a risk of immune reactions ranging from ones you'd never notice to anaphylactic shock. And for an untested compound, nobody can tell you which way it goes.
The FDA Panel Said Yes. That's Not the End.
This is where headlines have run ahead of the facts. In 2023, the FDA placed 19 peptide substances, including BPC-157, into "Category 2" — its list of bulk substances that may present significant safety risks, which in practice kept pharmacies from compounding them. It cited immunogenicity, impurities, problems characterising the ingredients and a lack of human safety data (National Law Review).
In 2026, the politics changed. On April 15, the FDA said 12 peptides were coming out of Category 2 after the groups that nominated them withdrew their nominations, and it scheduled advisory meetings to consider them (Orrick). As lawyers at the time pointed out, removal from Category 2 "does not, on its own, authorize use of that substance in compounding" (National Law Review).
On July 23 and 24, the FDA's Pharmacy Compounding Advisory Committee voted on seven of them. FDA scientists recommended against every one, citing insufficient safety, efficacy and characterisation data (FDA briefing; McDermott). The committee backed six anyway, most by two votes.
How the panel voted on letting pharmacies compound
Votes as reported by McDermott Will & Schulte and LumaLex Law (all seven), AJMC (all but Semax and Epitalon) and Time (BPC-157 and emideltide); BPC-157 count also confirmed by ABC News. FDA had not posted official minutes when we checked. FDA staff recommended against all seven. The votes are advice only: no peptide has been added to the list pharmacies may compound from.
Members who voted yes saw the risks as minimal; those who voted no worried that listing BPC-157 would give the false impression it had been evaluated like an approved drug (ABC News). One member, Dr. Elizabeth Rebello, told the meeting she was concerned "that we're responding to a market-induced demand rather than a decision based in solid science" (Time).
What happens next is slow. The FDA has to decide whether to accept the advice and then run notice-and-comment rulemaking (AJMC) to add any of these peptides to the "503A bulks list" — the substances pharmacies may compound from on a doctor's prescription. Lawyers tracking it expect that to take into 2027 or longer (McDermott), and the remaining peptides, including injectable GHK-Cu, are due at a second committee meeting before the end of February 2027 (National Law Review; Orrick).
How we got here, and what's next
| When | What happened |
|---|---|
| 2023 | FDA places 19 peptide substances, including BPC-157, in Category 2 over safety concerns |
| Dec 10, 2024 | FDA warning letter tells an online seller its "research use only" GLP-1s are drugs for human use |
| Feb 21, 2025 | FDA declares the semaglutide shortage resolved; compounders given until April 22 (pharmacies) or May 22 (outsourcing facilities) to stop making copies |
| Apr 15, 2026 | FDA announces 12 peptides coming out of Category 2 after nominations are withdrawn |
| Jul 23–24, 2026 | Advisory committee backs 6 of 7 peptides for compounding, against FDA staff advice |
| By end Feb 2027 | Second committee meeting on the remaining peptides |
| 2027 or later | Possible final rules adding peptides to the 503A bulks list |
Sources: National Law Review; FDA warning letter, December 10, 2024; FDA statement on GLP-1 compounding; Orrick; McDermott Will & Schulte; National Community Pharmacists Association.
The weight-loss copies are on a different track, and it's heading the other way. The FDA declared the semaglutide shortage over on February 21, 2025, which ended the exception that had allowed pharmacies to make mass copies (FDA). As of May 31, 2026, the agency had received 990 adverse event reports linked to compounded semaglutide and more than 730 linked to compounded tirzepatide. It has also had reports of adverse events, some requiring hospitalisation, that may be related to dosing errors with compounded injectable semaglutide (FDA). Reports like these don't prove the drug caused each problem, but the dosing-error pattern is a real risk when people measure their own doses from powder.
A Careful Man's Version
If you're tempted, start with the problem, not the peptide. (Our complete guide to peptides for men covers each compound in more depth.)
Talk to your doctor first — especially before injecting anything. Bring the name of what you're considering. A good doctor won't lecture you; they'll ask what you're trying to fix, and there's often a tested answer.
For weight loss, use an approved drug. This is where the gray market makes the least sense, because the real thing exists. Semaglutide (as Wegovy) and tirzepatide (as Zepbound) are FDA-approved for long-term weight management in adults with obesity, or overweight plus a weight-related condition (FDA; FDA). The FDA's advice is simple: "Patients should obtain a prescription from their doctor and fill the prescription at a state-licensed pharmacy." If cost is the obstacle, ask your doctor about the options rather than turning to a research website. Our piece on GLP-1s and muscle covers how to protect lean mass if you go that route.
For an injury that won't heal, get a diagnosis. A tendon that has hurt for months needs someone to find out why — imaging if needed, and a proper rehabilitation programme. Rehabilitation has been tested in people; injected BPC-157 for tendons hasn't.
For low energy, poor recovery or "low T", test before you treat. Growth-hormone peptides raise hormone levels without evidence that it helps healthy men. A blood test can tell you whether there's a real deficiency, which can be treated with approved medicines and proper monitoring. Strength training, sleep and protein remain the best-evidenced ways to build muscle after 40.
If you compete, don't. BPC-157 is banned under the World Anti-Doping Code, and USADA warns it is unknown whether there is a safe dose.
If you're already using something, tell your doctor exactly what and how much, so they can interpret your blood work and symptoms. Get urgent care if you develop a fever, a spreading or hot, painful injection site, or swelling and trouble breathing after a dose.
Frequently Asked Questions
Sources
- Mendias CL, Awan TM. Evaluation of research grade peptides marketed directly to consumers reveals extensive variability in purity and measured abundance. Preprints (April 24, 2026; not peer-reviewed). doi:10.20944/preprints202604.1748.v1. preprints.org
- Vasireddi N, Hahamyan H, Salata MJ, Karns M, Calcei JG, Voos JE, Apostolakos JM. Emerging use of BPC-157 in orthopaedic sports medicine: a systematic review. HSS Journal (2025). doi.org/10.1177/15563316251355551
- Teichman SL, Neale A, Lawrence B, Gagnon C, Castaigne JP, Frohman LA. Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295, a long-acting analog of GH-releasing hormone, in healthy adults. Journal of Clinical Endocrinology & Metabolism 91(3):799 (2006). academic.oup.com
- U.S. Food and Drug Administration. Certain bulk drug substances for use in compounding that may present significant safety risks (updated April 22, 2026). fda.gov
- U.S. Food and Drug Administration. Briefing document, Pharmacy Compounding Advisory Committee meeting, July 23–24, 2026. fda.gov (PDF)
- U.S. Food and Drug Administration. Warning letter to an online seller of "research use only" GLP-1 products (MARCS-CMS 695607, December 10, 2024). Searchable in FDA's warning letters database: fda.gov
- U.S. Food and Drug Administration. FDA's concerns with unapproved GLP-1 drugs used for weight loss (content current as of September 1, 2026). fda.gov
- U.S. Food and Drug Administration. FDA clarifies policies for compounders as national GLP-1 supply begins to stabilize. fda.gov
- Johns Hopkins Bloomberg School of Public Health. How the FDA regulates peptides — interview with Joshua Sharfstein (Public Health On Call, August 2026). publichealth.jhu.edu
- Salzman S, Kekatos M. FDA advisory committee votes to add popular peptide BPC-157 to drug compounding list. ABC News (July 23, 2026). abcnews.com
- Semuels A. An FDA committee just voted in favor of peptides — despite the agency's opposition. Time (July 23, 2026). time.com
- McDermott Will & Schulte. Bulk-list bound? PCAC backs majority of peptides in two-day public meeting (2026). mcdermottlaw.com
- LumaLex Law. The July 2026 PCAC peptide meeting (July 25, 2026). lumalexlaw.com
- AJMC. FDA panel backs 6 peptides for compounding (July 31, 2026). ajmc.com
- National Community Pharmacists Association. FDA advisory committee nominates six peptides for pharmacies to compound (July 31, 2026). ncpa.org
- Orrick. FDA announces removal of 12 peptides from Category 2 and schedules PCAC meetings (April 2026). orrick.com
- National Law Review. Tiny chains, big changes: what FDA's latest actions mean for peptide compounding (April 22, 2026). natlawreview.com
- Damon A. RFK Jr. may reverse a peptide ban he calls "illegal." Former FDA officials say he mischaracterized their work. ProPublica (April 3, 2026). propublica.org
- U.S. Food and Drug Administration. FDA approves new medication for chronic weight management (Zepbound). fda.gov
- U.S. Food and Drug Administration. FDA approves first treatment to reduce risk of serious heart problems specifically in adults with obesity or overweight (Wegovy; March 8, 2024). fda.gov
- Eli Lilly and Company. What to know about retatrutide (September 2026). lilly.com
- U.S. Anti-Doping Agency. BPC-157: experimental peptide creates risk for athletes (updated August 10, 2026). usada.org
The science is thin. The vial is a gamble.
Some of these peptides may yet prove useful. But today, BPC-157, TB-500 and their cousins are backed by animal studies and a handful of tiny human reports, and the vials sold online fail basic quality checks far too often to trust.
The 2026 panel vote is a step towards pharmacy-made versions, not proof they work, and it doesn't make a research vial legal. If you want faster healing, a leaner body or more energy, take the problem to your doctor. Where a tested, approved option exists, it is the better bet.


